The CAR-T Paradox: A Cure in the Clinic, a Crisis in the Supply Chain
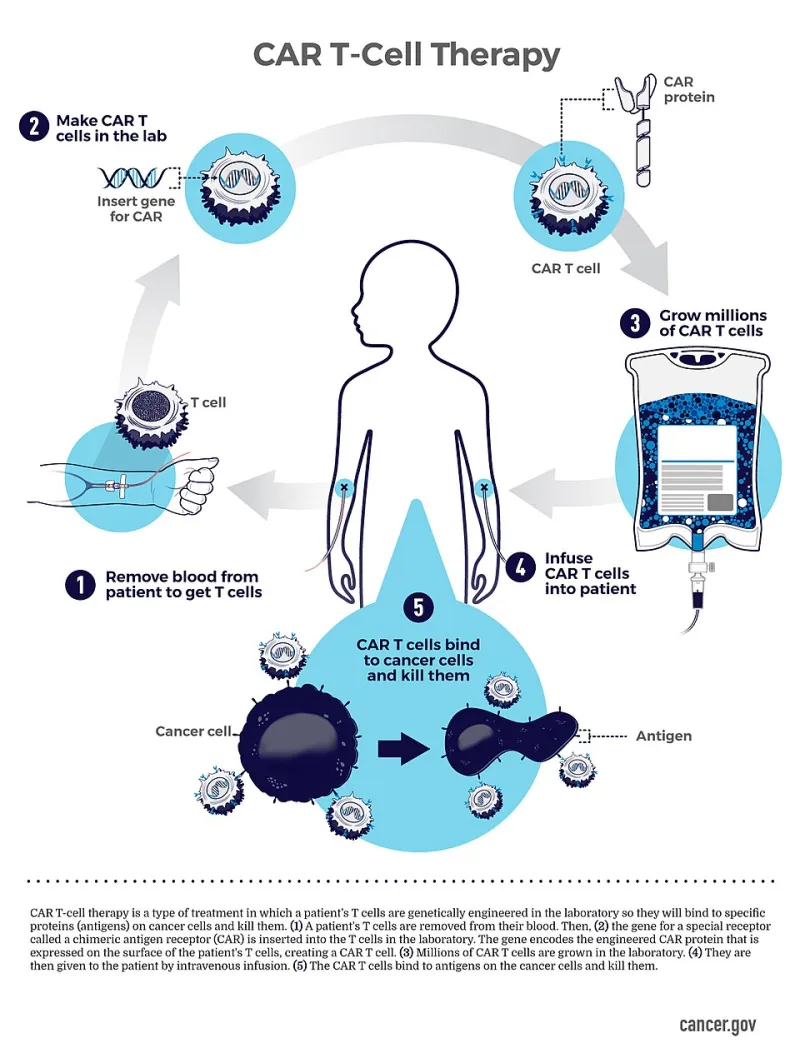
Photo: National Cancer Institute (NCI), Public domain, via Wikimedia Commons
In oncology, the word "remission" carries enormous weight. When applied to certain hematologic cancers—diffuse large B-cell lymphoma, acute lymphoblastic leukemia, multiple myeloma—it has historically come freighted with caveats: remission for now, remission pending further treatment, remission that statistics suggest will not last. Chimeric antigen receptor T-cell therapy, known broadly as CAR-T, has in select cases stripped away those qualifications entirely. Some patients have remained disease-free for years after a single infusion. In clinical parlance, the word being used with increasing, if still cautious, frequency is "cure."
And yet, as of this writing, the majority of Americans who might benefit from an approved CAR-T therapy will never receive one. The gap between what this technology can do and who actually receives it is not a matter of regulatory failure or scientific uncertainty. It is a structural problem embedded in how these therapies are made, priced, and delivered—and it is widening as new indications expand the eligible patient population faster than the infrastructure to serve them.
What CAR-T Actually Is—and Why It Is Hard to Make
Understanding the access problem requires understanding the manufacturing problem, and the manufacturing problem begins with biology. Unlike a small-molecule drug that can be synthesized in a reactor and dispensed in a pill, or even a monoclonal antibody produced in industrial cell culture vats, autologous CAR-T therapy is made from the patient's own immune cells.
The process begins with leukapheresis—drawing blood from a patient, separating out T-cells, and shipping those cells to a specialized manufacturing facility. There, the cells are genetically engineered using viral vectors to express a chimeric antigen receptor designed to recognize and destroy cancer cells bearing a specific surface protein. The modified cells are then expanded in culture, quality-tested, frozen, and shipped back to the treating institution, where they are infused into a patient who has undergone lymphodepleting chemotherapy to make room for the incoming army.
This process takes weeks. It requires ultra-cold chain logistics, specialized cleanroom manufacturing, and a level of quality control that is not merely regulatory formality—a batch failure means a patient with aggressive, rapidly progressing cancer waits longer, or does not receive treatment at all. Roughly five to ten percent of autologous CAR-T manufacturing runs fail to meet release specifications. For the patient whose cells are in that batch, that number is one hundred percent.
The Economics of Personalized Manufacturing
The cost structure that emerges from this process is almost without precedent in medicine. The six FDA-approved CAR-T products currently on the US market carry list prices ranging from approximately $370,000 to over $475,000 per infusion. When the costs of administration, hospitalization for toxicity management—cytokine release syndrome and neurotoxicity are common and occasionally severe—and supportive care are included, the total treatment episode frequently exceeds $700,000.
Payers, including Medicare and commercial insurers, have struggled to develop coherent coverage frameworks for therapies with this cost profile. Outcomes-based contracts, in which payment is partially contingent on whether a patient responds, have been piloted with limited success; the administrative infrastructure required to track long-term outcomes and adjudicate payments does not exist at meaningful scale. Some hospitals, particularly community oncology centers that lack the specialized programs required for CAR-T administration, simply do not offer the therapy at all, creating geographic deserts of access across large portions of the country.
For patients in rural America, or those whose insurance coverage is inadequate, or those whose disease progresses during the manufacturing window, the existence of a potentially curative therapy can be experienced as a kind of cruel proximity—close enough to know about, too far to reach.
The Allogeneic Hypothesis
The most frequently proposed solution to the manufacturing bottleneck is allogeneic, or "off-the-shelf," cell therapy. Rather than manufacturing a unique product from each patient's own cells, allogeneic approaches use engineered T-cells derived from healthy donors—cells that can be produced at scale, banked, and infused into any eligible patient much like a conventional drug.
The appeal is obvious. Allogeneic CAR-T could eliminate vein-to-vein time, reduce manufacturing costs by orders of magnitude, and make treatment available to patients whose disease is too aggressive to wait for autologous manufacturing. Several well-funded US biotechs—including Allogene Therapeutics, Precision BioSciences, and Fate Therapeutics—have been advancing allogeneic programs through clinical development.
The challenge is equally obvious. T-cells from a donor carry the risk of attacking the recipient's healthy tissue, a phenomenon called graft-versus-host disease. Conversely, the recipient's immune system may recognize and reject the donor cells before they have a chance to work. Early clinical data for allogeneic products have shown promising signals but have not yet matched the durability of response seen with the best autologous products. Whether the efficacy gap is a fundamental biological limitation or an engineering problem awaiting solution is the central question driving billions of dollars in research investment.
Regulatory Complexity as a Structural Barrier
The FDA has developed a sophisticated framework for cell and gene therapy regulation, and by most assessments the agency has worked constructively with developers to advance this field. But the regulatory requirements for these products—which are categorized as biologics and subject to extensive manufacturing standards under 21 CFR Part 1271—impose compliance costs that are proportionally far more burdensome for smaller developers and novel manufacturing approaches than for established pharmaceutical manufacturers.
The agency has acknowledged this tension and has published guidance documents aimed at facilitating development of innovative manufacturing technologies. Critics argue, however, that the pace of regulatory adaptation has not kept up with the pace of scientific innovation, particularly as developers explore decentralized manufacturing models—producing cell therapies closer to the point of care, rather than in centralized facilities—and automated, closed-system manufacturing platforms that could dramatically reduce costs and batch failure rates.
Decentralized manufacturing is perhaps the most disruptive concept circulating in the field. Companies including Lonza, Cellares, and several academic spinouts are developing automated manufacturing systems that could, in theory, be deployed at hospital sites, compressing the logistics chain and reducing the points of failure. These systems are not yet in widespread clinical use, and the regulatory pathway for decentralized CAR-T manufacturing remains incompletely defined.
The Startups Betting on a Different Architecture
Beyond allogeneic approaches and decentralized manufacturing, a third wave of innovation is attempting to sidestep the manufacturing problem altogether by eliminating the ex vivo cell engineering step. In vivo CAR-T—delivering the genetic instructions for a CAR directly into a patient's T-cells inside the body, using targeted viral vectors or lipid nanoparticles—would theoretically reduce the entire therapy to an infusion of an engineered delivery vehicle, manufacturable at scale like a conventional biologic.
This approach is earlier in development than either autologous or allogeneic CAR-T, and significant scientific questions remain about whether in vivo delivery can achieve the precision and potency required for therapeutic effect. But companies including Umoja Biopharma and a handful of university-based programs have published early data suggesting the concept is not merely theoretical.
A Field at an Inflection Point
Cell therapy occupies a peculiar position in the landscape of American medicine. It has produced some of the most compelling clinical outcomes in modern oncology. It has attracted extraordinary investment—billions of dollars from venture capital, large pharmaceutical acquirers, and the federal government through programs at the National Cancer Institute and the Advanced Research Projects Agency for Health. And it remains, for the majority of patients who need it, effectively inaccessible.
That paradox is not permanent. The manufacturing, regulatory, and economic barriers that define today's landscape are real, but they are not immutable. Each of the approaches described here—allogeneic platforms, decentralized manufacturing, in vivo delivery—represents a credible path toward a version of cell therapy that is available not only in the specialized academic medical centers of Boston, Houston, or New York, but in the community oncology practices where most Americans with cancer actually receive their care.
The timeline for that transition is uncertain. What is certain is that the scientific achievement these therapies represent will remain morally incomplete until the patients who need them can actually get them.